
A painful, swollen ankle after a twist, a fall, or a knock during sport can mean either a sprain or a fracture. The two can feel remarkably similar, especially in the first hours after the injury. That's why so many broken ankles are mistaken for sprains at first. An ankle fracture is a break in one or more of the three bones that form the ankle joint: the tibia, the fibula, and the talus. Some fractures are stable and heal well with immobilisation alone. Others involve the joint shifting out of position and may need surgical fixation to restore normal alignment and function.
Understanding Ankle Fracture
Ankle fractures are classified by which of the three ankle bones is broken and where. A break in the fibula is called a lateral malleolus fracture, a break in the tibia is a medial malleolus fracture, and a break at the back of the tibia is a posterior malleolus fracture. When two of these break together, it is called a bimalleolar fracture, and when all three break, it is trimalleolar. Some fractures also involve the syndesmosis, the strong ligament joining the tibia and fibula just above the ankle joint. This can change the treatment plan even when the fracture itself looks straightforward. The most common causes are twisting injuries on uneven surfaces, falls from standing height or higher, direct blows during contact sport, and road traffic collisions.
You usually can’t tell from symptoms alone if it's a break or a sprain. An ankle sprain and a stable fracture can produce very similar pain and swelling in the first few hours, and X-ray is the standard way to tell the difference, sometimes supported by a CT scan for more complex fracture patterns. A private consultation means you can be assessed, imaged, and started on a treatment plan quickly rather than waiting to find out what is wrong. For patients with private medical insurance, treatment including imaging and surgery where needed is typically covered. Self-funding patients can be seen at short notice at four central London clinic locations.
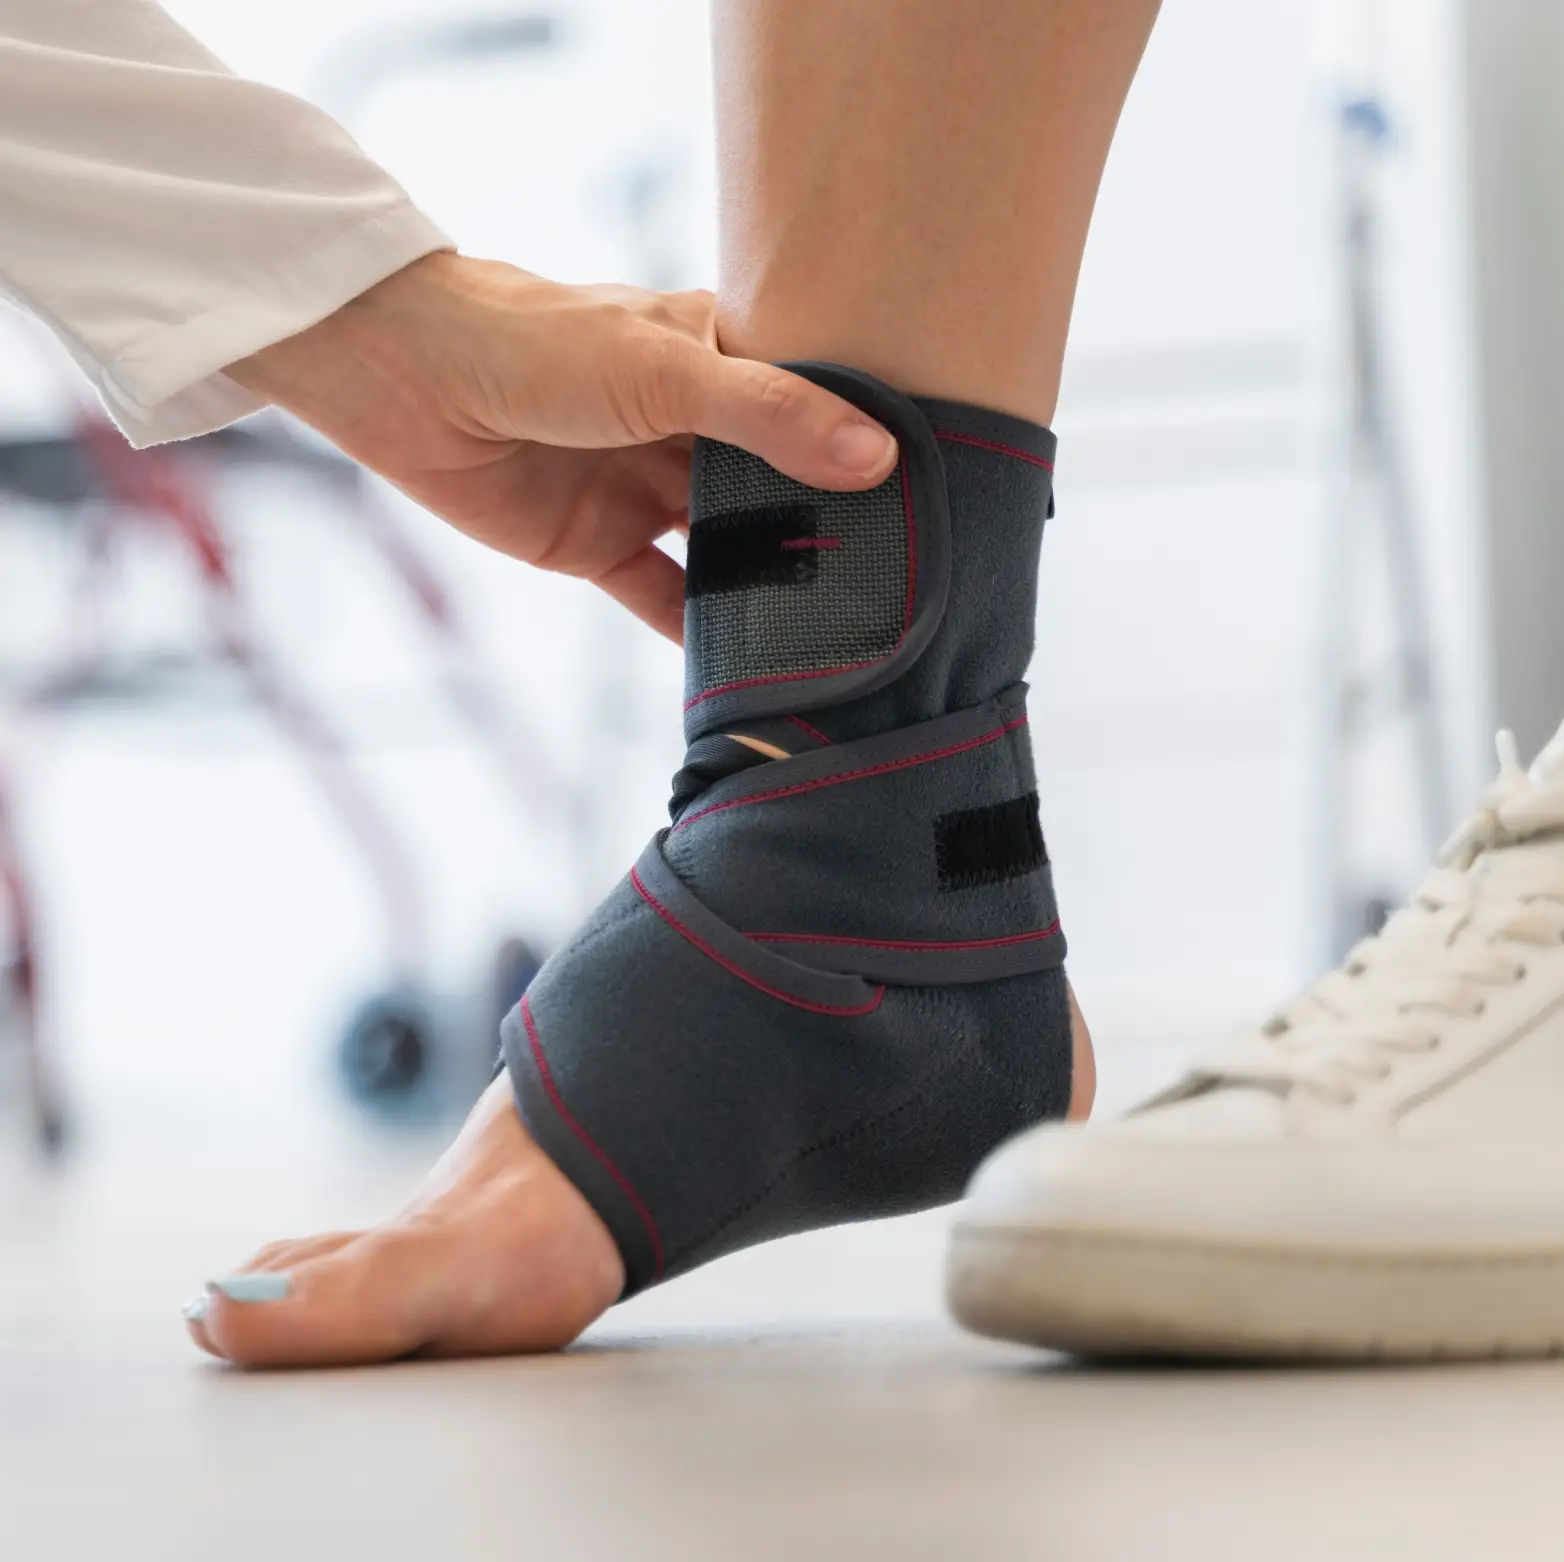
Symptom Checklist
Symptoms vary depending on which bones are involved and how displaced the fracture is. Tick anything that applies to you.
Seek immediate attention at your nearest A&E department if the foot is deformed, cold, pale, numb, or the skin is broken. Otherwise, get a clear diagnosis at short notice.
Treatment Pathway
The right treatment depends on which bones are broken, how displaced the fracture is, and whether the ankle joint remains stable. At every stage, the goal is to restore a stable, well-aligned joint using the least invasive approach that reliably achieves it.

Prompt diagnostic imaging confirms which bones are broken and whether the joint is stable. This is done while protecting the ankle and managing the pain.
X-ray and CT where needed
Splinting or boot immobilisation
Pain and swelling management

Many ankle fractures are stable and do not involve significant joint displacement. These are usually managed without surgery.
Cast or boot immobilisation
Staged, protected weight-bearing
Physiotherapy-led rehabilitation

Surgery is recommended when the fracture is displaced, unstable, or involves the joint surface. A joint that heals out of position is more likely to develop early arthritis.
Open reduction and internal fixation
Syndesmosis repair where needed
Protected rehabilitation programme
LMS, PhD. Consultant Trauma and Orthopaedic Surgeon. Foot and Ankle Specialist.
Consultant at The Royal London
Board member, GRECMIP
Honorary Senior Lecturer
Mr Malagelada is a fellowship-trained Consultant Orthopaedic Surgeon specialising exclusively in conditions of the foot and ankle. He trained in Spain and the UK, including at the Royal National Orthopaedic Hospital and the Royal London, and holds a BOFAS-accredited Foot and Ankle fellowship. He has been a Consultant at The Royal London Hospital since 2017, where he also teaches on the MSc in Orthopaedic Trauma Sciences.

Patient Stories
Real outcomes, independently verified on Doctify.
It depends on which bones are broken and whether surgery is needed. A stable fracture treated in a cast or boot typically heals enough for protected weight-bearing within six weeks. After surgical fixation, most patients are walking in a boot by around six weeks. Full recovery, including return to sport, usually takes three to four months. Your specific timeline will be discussed at your consultation.
No. Many ankle fractures are stable, meaning the joint hasn't shifted out of position. These heal well with cast or boot immobilisation alone. Surgery is recommended when the fracture is displaced, unstable, or involves the joint surface, since an ankle that heals in the wrong position is more likely to develop early arthritis.
Not safely, and not until you have been assessed. Some patients manage a few painful steps even with a fracture present. That's why fractures are so often mistaken for sprains. Your surgeon will confirm weight-bearing status on examination and imaging. Walking on an unstable fracture before it is protected can make the injury worse.
The most common procedure is open reduction and internal fixation. The fracture is realigned and held in place with plates and screws while it heals. If the syndesmosis ligament is damaged, surgeons repair or stabilise it at the same time. The procedure is planned around your specific fracture pattern and is discussed in detail at your pre-operative consultation.
This varies more between individuals than general recovery guides suggest. It depends on the fracture pattern, whether you needed surgery, and the demands of your sport. As a general guide, you can often resume low-impact activity after around eight to twelve weeks. Higher-impact and contact sports typically take longer. Your surgeon will give you a realistic timeline once follow-up imaging has confirmed healing.
No. If you are paying for your own care, you can contact the clinic directly, and appointments are usually available at short notice. If you have private health insurance, most major UK insurers, including Bupa, AXA Health, Aviva, Vitality, WPA, and Cigna, do not require a GP referral to see a private orthopaedic consultant for an ankle fracture. It is always worth confirming your individual level of cover with your insurer before your appointment.
Still have questions?
Send a question using the form below. A member of the team will reply within one working day.
